What the Anion Gap Assesses
The anion gap is a calculated value that assists clinicians in evaluating acid-base balance and identify hidden metabolic acidosis. It is not directly measured on a lab report, but it is derived from standard electrolytes in a serum chemistry panel. In practice, the anion gap helps show whether there are unmeasured anions contributing to an acid-base disorder.
Most often, the anion gap is used alongside other lab results to support a diagnostic evaluation. It can help distinguish between different types of acid-base problems, guide the next steps in treatment, and clarify whether a patient’s serum chemistry is pointing toward a metabolic derangement. Because the result depends on several lab values, understanding the relationship between sodium, chloride, and bicarbonate is essential.
The anion gap calculator becomes especially useful when you want to quickly calculate anion gap from a electrolyte panel. While the number itself is simple, the meaning behind it depends on the broader clinical picture. A change in the anion gap may reflect acid accumulation, loss of bicarbonate, or shifts in chloride that alter the overall acid-base analysis.
How to Work with the Anion Gap Calculator
To use an anion gap calculator, you need the essential values from a routine lab panel: sodium, chloride, and bicarbonate. A few formulas also include potassium, though many common clinical calculations leave potassium out because it contributes less to the final result. The calculator follows a standard anion gap formula to calculate the difference between measured cations and measured anions.
The most common formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
In some settings, potassium is factored in:
Anion gap = Sodium + Potassium - (Chloride + Bicarbonate)
Both versions are based on the same principle: the body maintains electrical neutrality, so the measured positive and negative ions should offset each other. Any gap suggests the presence of other ions not directly shown on the routine lab results. Those hidden ions often include acids or additional substances that matter in acid-base disorders.
When using the calculator, make sure the values come from the same blood sample and the same time point whenever possible. Small changes in the numbers can affect the result, especially when there is already a borderline abnormality. A reliable calculation is only the first step; the next step is thoughtful clinical interpretation in context.
Why Blood Bicarbonate Matters
Serum bicarbonate is essential for the assessment of acid-base status because it reflects one of the main buffers in the blood. On many lab reports, bicarbonate appears as CO2, which usually means total CO2 content and serves as a practical estimate of bicarbonate. A low serum bicarbonate level often points to bicarbonate depletion and may indicate metabolic acidosis, while a higher value may indicate metabolic alkalosis.
Because bicarbonate is included directly in the anion gap formula, it has a dual role. It helps determine whether the gap is abnormal, and it also provides clues about the underlying acid-base pattern. For example, when bicarbonate falls, the body may be depleting buffer to neutralize excess acid. That decline may be accompanied by a rise in the anion gap if unmeasured acids are building up.
Bicarbonate also helps identify compensation. In an acid-base disorder, the body often tries to restore balance through respiratory or renal adjustments. A low bicarbonate level may be paired with changes in CO2 on a blood gas, suggesting a compensatory response rather than a separate issue. That is why serum bicarbonate should not be interpreted alone.
When a clinician reviews a lab value labeled CO2, it is important to note that it is part of the broader acid-base picture. The result can shift due to vomiting, diuretics, renal dysfunction, severe diarrhea, or acid accumulation. The relationship between bicarbonate and the anion gap helps interpret the pattern more clearly.
Typical Interval and Meaning
A normal anion gap typically lies within a laboratory-specific normal range. The precise interval may differ depending on the instrument and whether potassium is included in the formula. Since lab methods are different, assessment should always use the reference value provided by that laboratory rather than relying on a single universal cutoff.
A within-range result does not always mean everything is normal, and an abnormal result does not always mean serious disease. The context matters. As an example, a patient with hypoalbuminemia may have a deceptively normal or low anion gap even when a substantial acid load is present. As albumin is a major unmeasured anion, changes in albumin can shift the expected result.
This is why the albumin-corrected anion gap is important. The correction modifies the calculation so that low albumin does not mask an elevated gap. In many cases, the corrected value gives a more reliable picture of the patient’s real acid-base status. It can reveal a occult anion gap acidosis that would otherwise be missed.
Evaluating the result means looking beyond a single number. Check whether the patient has acidosis or alkalosis, whether the bicarbonate level is low or high, and whether albumin is abnormal. These details shape the overall clinical evaluation and determine whether additional testing is warranted.
High Anion Gap vs Typical Anion Gap Acidosis
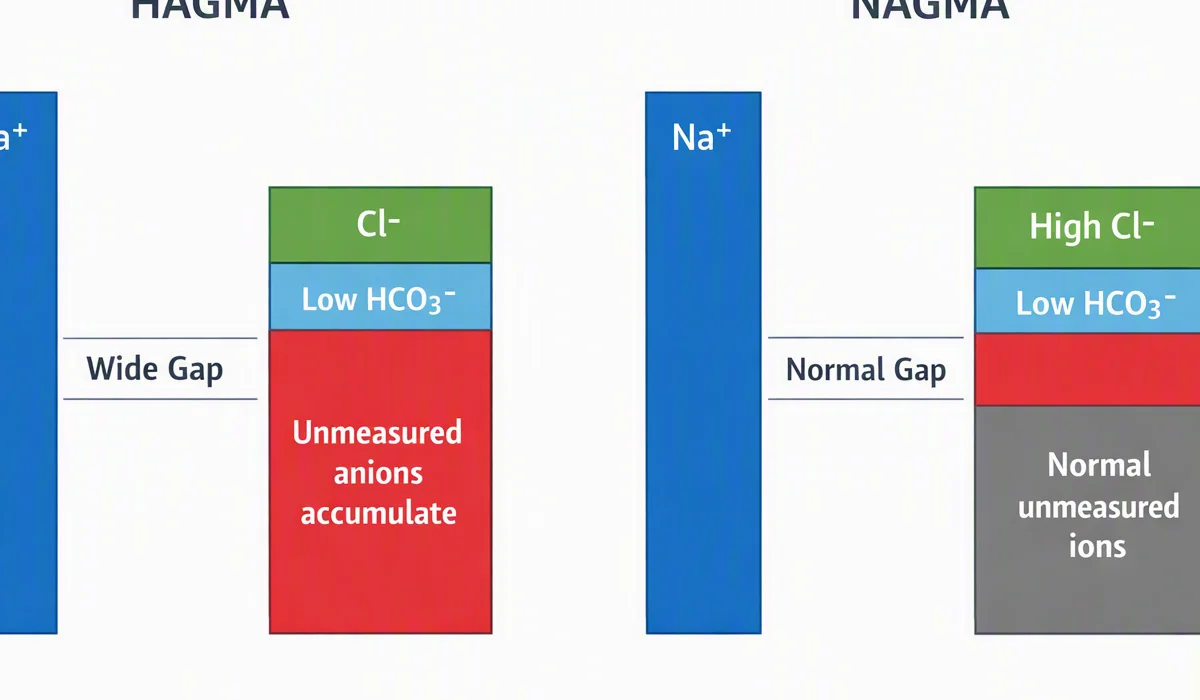
A elevated anion gap metabolic acidosis means that acids are accumulating in the body and adding extra unmeasured anions. In this setting, bicarbonate is often consumed as it buffers excess acid. Typical causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The elevated gap is a clue that the bicarbonate drop is not just from loss or dilution, but from acid generation or retention.
By contrast, normal anion gap metabolic acidosis often occurs when bicarbonate is lost and chloride rises to maintain electrical balance. This is often called hyperchloremic acidosis. The anion gap remains within the reference range because the decrease in bicarbonate is offset by an increase in chloride. That pattern is very different from a high-gap state, even though both involve acidosis.
The distinction matters because the differential diagnosis varies based on the pattern. High-gap acidosis suggests acid accumulation or impaired clearance, while normal-gap acidosis points more toward bicarbonate loss, renal tubular problems, or chloride-rich fluid administration. The calculator helps identify the pattern, but the clinician still needs to connect it to the rest of the lab results and the patient’s presentation.
In real practice, a single patient may have more than one process at once. For example, someone can have lactic acidosis and also a normal-gap process from diarrhea. That is why acid-base analysis often requires more than one calculation and a careful review of the full clinical story.
Typical Causes of Unusual Results
Multiple conditions can lead to an elevated anion gap. A particularly common is lactic acidosis, where reduced oxygen delivery, shock, sepsis, seizures, or other stressors lead to lactate accumulation. The lactate represents unmeasured acid and can significantly raise the anion gap while reducing bicarbonate.
Ketoacidosis is an additional frequent cause. It may occur in diabetic ketoacidosis, alcohol-related states, or starvation. In these settings, ketone bodies accumulate and consume bicarbonate as the body attempts to buffer the acid load. The result is often a typical high anion gap pattern with low serum bicarbonate.
Renal failure can also increase the gap because the kidneys cannot remove acids effectively. As kidney function declines, retained organic acids and reduced excretion of hydrogen ions contribute to metabolic acidosis. This can produce a significant change in the lab results, especially when the disorder is advanced.
Toxic alcohols are important to consider because they can produce marked high-gap acidosis and require urgent attention. Methanol, ethylene glycol, and similar substances generate acidic metabolites that increase the gap and may be accompanied by other clinical clues. In these cases, the anion gap calculator becomes part of a wider emergency assessment rather than a stand-alone answer.
Additional causes can include severe tissue hypoperfusion, medications, and mixed disorders. Because many abnormalities overlap, the anion gap should be viewed as a starting point for a larger diagnostic evaluation rather than a final diagnosis.
How Albumin Alters the Reading
Albumin is one of the main unmeasured negatively charged particles in blood, which means it has a major effect on the anion gap. When albumin is low, the gap may appear falsely typical or only mildly increased even when there is clinically important acid accumulation. This is where hypoalbuminemia can make interpretation deceptive.
The solution is albumin correction. The corrected anion gap adjusts the result to account for low albumin, giving a more accurate estimate of the patient’s true acid-base state. Because albumin carries a negative charge through protein binding, a decrease in albumin reduces the expected baseline gap. If that is ignored, the abnormality may be underestimated.
Albumin correction is especially important in patients who are critically ill, malnourished, inflamed, or hospitalized for prolonged periods. In these settings, a “normal” result may not be comforting. A corrected value may reveal high-gap acidosis that changes treatment decisions.
For this reason, albumin should be part of the broader clinical interpretation whenever the gap and bicarbonate do not seem to match the expected pattern. If the lab result looks unclear or inconsistent, checking albumin can help avoid missed diagnoses.
When to Seek Further Testing
An anion gap result is often most helpful when paired with other evaluations. If the patient has symptoms, abnormal vital signs, or unclear lab findings, additional testing may be needed to identify the acid-base disorder. An arterial blood gas can measure pH, carbon dioxide, and oxygenation, while a venous blood gas can provide useful acid-base information in many situations with less invasiveness.
A lactate level is important when lactic acidosis is suspected, especially if the patient has signs of poor perfusion, infection, or severe illness. Lactate helps show whether the high gap reflects tissue hypoxia, impaired clearance, or another metabolic issue. It is often ordered alongside a repeat electrolyte panel or other laboratory studies.
A basic metabolic panel is a typical starting point because it includes the electrolytes needed to calculate the gap and the bicarbonate value needed for interpretation. Depending on the case, clinicians may also order glucose, ketones, kidney function tests, or toxicology studies. Those tests help define the underlying cause rather than just confirming that a problem exists.
If the gap is abnormal but the picture is unclear, repeating the labs and reviewing timing, hydration status, and medication exposure can be helpful. The goal is to connect the lab pattern to the patient’s condition and move from screening to a clear diagnosis.
FAQs About Anion Gap and Bicarbonate
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the difference between measured cations and anions in the blood, usually More helpful hints from sodium, chloride, and bicarbonate values. It helps assess acid-base disorders, especially metabolic acidosis, and supports clinical interpretation of routine lab results. The calculator is a quick tool for spotting patterns that may need further evaluation.
How do you calculate the anion gap with serum bicarbonate?
To calculate the anion gap with serum bicarbonate, use the standard formula: sodium minus the sum of chloride and bicarbonate. In equation form, it is anion gap = sodium - (chloride + bicarbonate). Some formulas also include potassium, but many clinical settings use the simpler version. The bicarbonate value is required because it is part of the calculation and also reflects the acid-base state.
What can a low or high anion gap mean?
A low anion gap can result from low albumin, lab variation, or in some cases other conditions that alter measured ions. A increased anion gap usually indicates the presence of unmeasured acids and may point to high anion gap metabolic acidosis. The next step is to assess the result with bicarbonate, albumin, and the clinical picture to determine the likely cause.
Why is albumin correction matter when evaluating the anion gap?
Albumin is a major unmeasured anion, so hypoalbuminemia can decrease the expected gap and hide an abnormality. Albumin correction adjusts the result to account for this effect and supports clinical interpretation. Without correction, a patient with significant acidosis may appear to have a normal result.
Can a normal anion gap still occur with metabolic acidosis?
Yes. A normal anion gap metabolic acidosis can occur when bicarbonate is lost and chloride rises to balance the charge, creating hyperchloremic acidosis. This means metabolic acidosis is present even though the gap stays within the reference range. That is why reviewing bicarbonate, chloride, and the full electrolyte pattern is so important for accurate diagnosis.